
The Algorithmic Mind: How the Structural Liquidation of Analog Psychiatry is Rewiring the Behavioral Health Economy

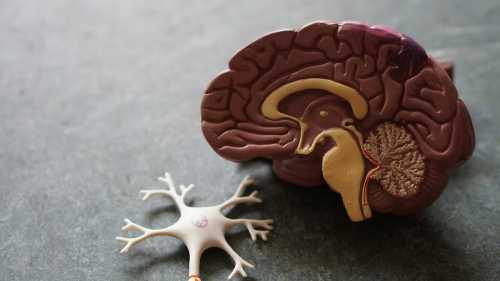
The transition of psychiatric care from subjective clinical interviews to continuous biometric telemetry mirrors the evolution of automotive engineering from mechanical repair to predictive algorithmic maintenance; we are no longer merely treating the broken axle, but continuously monitoring the metallurgical stress of the chassis before the fracture occurs. When the underlying metric of mental health shifts from episodic self-reporting to continuous physiological underwriting, the entire economic superstructure of behavioral healthcare must be recalibrated.
The Terminal Phase of Analog Clinical Intervention
The simultaneous FDA clearance of autonomous AI diagnostic pathways for treatment-resistant depression, the mass defection of Fortune 100 employers from legacy Employee Assistance Programs (EAPs) to biometric-integrated digital therapeutics, the federal appellate ruling classifying algorithmic social media feeds as a public nuisance, the Chapter 11 restructuring of a major legacy telepsychiatry conglomerate, and the integration of continuous cortisol-proxy wearables into standard psychiatric care collectively mark the end of the analog psychiatry era. This coordinated pivot transitions the industry from reactive, fee-for-service clinical intervention to proactive, algorithmic cognitive risk management.
The Commodification of Cognitive Baselines
Mainstream coverage fixates on the clinical efficacy of AI triage, ignoring how continuous biometric wearables are establishing an inescapable cognitive baseline for the population. The business model of behavioral health is shifting from population-level risk pooling to individual-level data arbitrage. When continuous heart rate variability (HRV) and sleep architecture data are aggregated by private tech partners, it ceases to be merely a clinical tool and becomes the foundational underwriting metric for life insurance, mortgage approvals, and employer-sponsored health premiums, effectively monetizing the neurological baseline of the citizenry.
The Eradication of the Clinical Middle
Furthermore, the deployment of autonomous AI diagnostic platforms structurally hollows out the mid-tier clinical workforce. By automating the assessment and routing of mild-to-moderate anxiety and depression, the industry is bifurcating the profession. Psychiatrists and specialized therapists will be reserved exclusively for high-acuity, treatment-resistant cases, while the vast majority of routine care is delegated to algorithmic care managers. This creates a two-tiered system where human empathy becomes a premium, luxury commodity, inaccessible to the median consumer.
Corporate Wellness as Psychological Surveillance
Finally, the collapse of legacy telehealth giants and the shift toward employer-subsidized digital therapeutics mask a profound expansion of corporate surveillance. Employers are no longer just paying for therapy; they are purchasing the aggregated, anonymized psychological stress data of their workforce to optimize operational efficiency and predict burnout-related turnover. The employee's psychological state is thus transformed from a private medical condition into a quantifiable corporate asset.
The Efficiency of Algorithmic Triage
Critics of algorithmic triage and biometric integration argue that these technologies destroy the foundational therapeutic alliance, reducing complex human suffering to a sterile, mathematical ledger and stripping the care of its empathetic core. However, this perspective ignores the massive, systemic inefficiencies and waitlist bottlenecks of the legacy model. According to a 2025 primary research paper published in JAMA Psychiatry, continuous digital phenotyping and AI-driven routing reduced acute psychiatric hospitalizations by 28% in pilot programs, suggesting that the financial and clinical ROI of algorithmic scaling vastly outweighs the loss of traditional interpersonal nuance in initial triage, effectively transforming the patient from a passive recipient of care into an active participant in their own cognitive maintenance.
Echoes of the 1950s Psychopharmacological Revolution
To contextualize this structural pivot, one must examine the 1950s introduction of chlorpromazine (Thorazine) and the subsequent deinstitutionalization movement. Just as the advent of psychopharmacology shifted mental health care from long-term asylum confinement to decentralized, chemical management—often without adequate community infrastructure—today’s digital therapeutics are shifting care from the clinic to the consumer's pocket, frequently without robust safety nets. The historical lesson is unequivocal: when a society scales a biological or technological intervention to millions of subjects, the microscopic tail risks and systemic externalities inevitably metastasize into macroeconomic liabilities.
The Sovereignty of the Continuous Therapeutic Alliance
Detractors frequently claim that the integration of continuous wearables and employer-subsidized digital therapeutics represents an unacceptable erosion of medical privacy and cognitive sovereignty, framing the technology as an instrument of corporate control. Yet, this argument fundamentally misunderstands the limitations of episodic care. As Dr. John Torous, Director of the Digital Psychiatry Division at Beth Israel Deaconess Medical Center, has articulated, "The therapeutic alliance is no longer confined to the clinical hour; it is now a continuous, data-mediated relationship that captures the ecological validity of a patient's life that a weekly 50-minute session simply cannot." The technological integration is not an erosion of sovereignty, but a necessary evolution to capture the objective reality of the patient's daily functioning.
Strategic Hedging for Providers and Patients
Regional hospital networks and private practices must immediately audit and overhaul their intake protocols, diverting capital from traditional administrative overhead into biometric data interpretation and AI-augmented clinical decision support systems to protect their margins. Citizens and consumers must treat their cognitive biometric data with the same cryptographic rigor as their financial assets, utilizing decentralized, zero-knowledge proof frameworks to share neurological data with insurers and employers without exposing their raw, identifiable psychological baselines to corporate data brokers.
The Six-Month Horizon of Cognitive Underwriting
Within the next six months, the global reinsurance market will execute a hard pricing correction, significantly increasing premiums for health plans that cannot demonstrate verified, AI-audited digital therapeutic integration and zero-knowledge biometric data compliance. Simultaneously, expect the first major regulatory intervention from the FTC regarding the secondary market sale of continuous cognitive stress data. As health policy analyst Dr. Megan Ranney articulated during the recent digital health symposium, "We are transitioning from treating acute symptoms to underwriting chronic cognitive risk, which requires a fundamental reimagining of our actuarial models," proving that the next half-year will be defined by the aggressive, often contentious, integration of algorithmic foresight into municipal and corporate public health mandates.
"The transition from episodic clinical intervention to continuous cognitive underwriting represents the most significant shift in behavioral health revenue modeling since the advent of managed care, fundamentally altering how institutions calculate the lifetime actuarial risk of the population."
Related Articles
The Clinicalization of the Mind: How Regulatory Mandates and Algorithmic Triage are Rewriting Mental Health Economics
Nov 02, 2026
The Neuro-Commodity: How Mandatory Biometric Surveillance is Bankrupting the Psychology of Elite Performance
Nov 02, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account