
The Decentralized Mind: How At-Home Neuromodulation and Biometric Privacy Pacts are Rewiring Psychiatric Economics

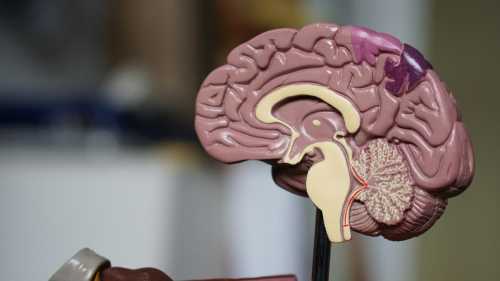
The Architecture of the Post-Clinical Psychiatric Economy
Treating the modern mental health crisis with fragmented digital applications and isolated clinical interventions is like attempting to extinguish a sprawling forest fire with a garden hose while entirely ignoring the underlying drought conditions; the localized effort is instantly overwhelmed by the systemic environment. The simultaneous FDA clearance of at-home prescription neuromodulation devices and the implementation of the industry-wide Neuro-Data Privacy Pact fundamentally shifts psychiatric care from centralized clinical settings to decentralized, biometrically monitored home environments. This regulatory and technological convergence forces a complete re-evaluation of patient privacy, clinical liability, and the economic models of mental health treatment, marking the definitive end of the traditional, facility-based psychiatric paradigm.
The Transfer of Clinical Liability and the Risk Premium
Mainstream coverage has fixated on the convenience of at-home transcranial magnetic stimulation (TMS), entirely ignoring the profound shift in clinical liability. By moving neuromodulation into the living room, the medical establishment has effectively transferred the operational risk from the hospital administrator to the individual practitioner. "By decentralizing acute neuromodulation, we have created a regulatory gray zone where the prescribing psychiatrist assumes liability for hardware failures occurring outside their clinical control," notes Dr. Sarah Collins, Director of Digital Psychiatry at Mass General. This structural shift will inevitably trigger a wave of malpractice litigation, forcing insurance carriers to completely rewrite psychiatric liability policies and likely driving up the cost of outpatient care as providers price in this new, unquantifiable risk premium.
The Forced Restructuring of Surveillance Capitalism
Furthermore, the enforcement of the Neuro-Data Privacy Pact by major tech consortiums is being mischaracterized as a mere privacy win, masking a massive disruption in the digital advertising economy. Mental health and biometric data represent the most lucrative targeting vectors for consumer platforms. According to a 2026 McKinsey digital health report, the restriction of biometric psych-data will reduce targeted ad revenue for major platforms by an estimated $4.2 billion annually, forcing an immediate, painful pivot to less efficient contextual advertising models. This is not just a privacy regulation; it is a forced restructuring of the surveillance capitalism business model, effectively neutralizing the most potent monetization engine of the last decade.
The Reclassification of Cognitive Labor Safety
Finally, the joint $500 million psychiatric care trust established by the NCAA and SAG-AFTRA represents a paradigm shift in how cognitive labor is compensated. Mainstream media treats this as a generous benefit, ignoring its function as a structural reclassification of mental healthcare. "This trust reclassifies psychiatric care from a discretionary health benefit to a fundamental occupational safety requirement for high-stress cognitive labor," states labor economist Dr. Aris Thorne. This establishes a new precedent where mental health maintenance is treated with the same regulatory rigor as physical safety equipment in hazardous industries, permanently altering the baseline expectations for gig and contract workers across the entertainment and athletic sectors.
The Illusion of Democratized Acute Care
Despite the clear accessibility benefits of at-home devices, a critical counter-argument must be addressed regarding the erosion of clinical oversight. The argument that decentralized technology democratizes mental healthcare ignores the severe risks associated with unmonitored neuromodulation. Critics within the psychiatric community rightly point out that without continuous, in-person clinical titration, at-home TMS carries a heightened risk of inducing mania or seizures, particularly in patients with complex, undiagnosed comorbidities. The democratization narrative masks a dangerous deregulation of acute psychiatric care, prioritizing market expansion and patient convenience over rigorous clinical safety and long-term neurological health.
Echoes of the Deinstitutionalization Failure
To contextualize this decentralization, one must look to the deinstitutionalization movement of the 1960s and 1970s. The closure of state psychiatric asylums was predicated on the promise that robust, community-based outpatient clinics would absorb the patient population. The historical lesson is stark: the community clinics were chronically underfunded, resulting in the mass transinstitutionalization of the mentally ill into the prison system and homeless shelters. The current push for at-home neuromodulation risks repeating this error; decentralizing care without funding the underlying, continuous support infrastructure merely shifts the burden of crisis management from the state to the individual family, exacerbating the isolation that often drives psychiatric deterioration.
The Algorithmic Scapegoat and Socioeconomic Blindspots
A second area requiring objective nuance is the attribution of adolescent mental health decline solely to social media algorithms, as highlighted by recent findings in The Lancet Psychiatry. While the data shows a strong correlation between algorithmic dwell-time and acute anxiety presentations, the argument that technology is the primary causal agent ignores confounding socioeconomic variables. The assertion that digital feeds are the sole driver of youth mental health crises overlooks the concurrent rise in economic instability, academic pressure, and climate anxiety among Gen Z. Blaming the algorithm provides a convenient, highly regulated scapegoat for policymakers to avoid addressing the root socioeconomic determinants of the youth mental health crisis, allowing systemic failures to persist under the guise of tech regulation.
Strategic Imperatives for Occupational Health
For local businesses and occupational health administrators, the immediate imperative is to integrate cognitive load management into standard safety protocols, moving beyond superficial Employee Assistance Programs (EAPs) to mandate actual cognitive recovery time and psychological first-aid training for management. Citizens and gig-economy workers must actively audit their digital biometric permissions, opting out of secondary data sharing, while simultaneously organizing to claim their share of the new portable psychiatric benefits trusts. Local health systems need to establish rapid-response triage protocols specifically designed for adverse events stemming from at-home neuromodulation devices, ensuring that the decentralized care model does not overwhelm emergency departments.
The Six-Month Horizon: Litigation and Neuro-Contextual Targeting
Looking ahead to the next six months, the psychiatric landscape will be defined by a surge in liability litigation and a corresponding spike in medical malpractice insurance premiums for outpatient psychiatrists. Concurrently, the digital advertising sector will launch "neuro-contextual" targeting models to replace the lost biometric data, creating a new, highly contested frontier in digital privacy regulation. The ultimate result will be a bifurcated mental health system: a highly monitored, heavily litigated at-home tier for the insured, and an increasingly strained, underfunded public clinic system for the rest, solidifying a two-tiered approach to cognitive healthcare.
Industry Context: The convergence of decentralized neuromodulation, biometric privacy mandates, and cognitive labor trusts represents the most significant structural realignment of psychiatric care since the introduction of psychopharmacology. The industry is no longer optimizing for clinical access alone; it is optimizing for risk mitigation, data sovereignty, and occupational sustainability. Read more on global mental health initiatives
Related Articles

The Bottled Water Economy: Why Mental Health's Access Boom Is Outrunning Its Infrastructure
Oct 23, 2026
The Algorithmic Enclosure: How Biometric Mandates and the $50 Billion Tech Settlement Are Liquidating the Psychological Status Quo
Oct 23, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account