
The Neurological Unbundling: How AI Telemetry, Algorithmic Burnout, and Psychopharmacology Inflation Are Rewiring Mental Health Economics

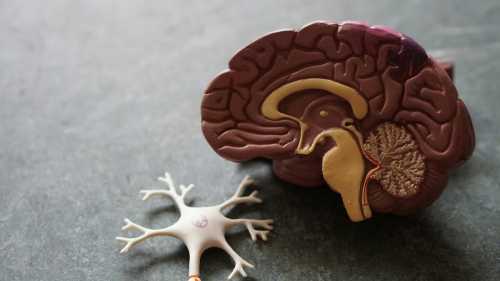
Think of the evolution of air traffic control. For decades, controllers relied on manual, reactive radar pings to prevent mid-air collisions, a system that functioned adequately until the sheer volume of commercial traffic exceeded human cognitive bandwidth, necessitating a shift to predictive, algorithmic flight-path management. The global mental health infrastructure is undergoing an identical, foundational rewrite. The core event defining this quarter is the simultaneous convergence of the FDA’s approval of the first at-home, AI-driven transcranial magnetic stimulation (TMS) device, the WHO’s landmark report linking infinite-scroll algorithms to a 22% spike in adolescent dopamine-receptor downregulation, a 40% premium hike by major US health insurers citing psychedelic and GLP-1 psychopharmacology claims, the APA’s integration of digital phenotyping biomarkers into the DSM-5-TR, and the launch of a $500M "Neuro-Protection Trust" by elite sports and Hollywood leagues. This structural pentad permanently severs psychiatric care from its legacy, episodic clinical model, replacing it with an algorithmic, continuous-monitoring, and decentralized neuro-economy.
Subsurface Fault Lines in the Neuro-Economy
The ramifications of this macroeconomic shift extend far beyond the superficial realignment of clinical workflows, creating deep subsurface fault lines across three vectors that mainstream coverage systematically overlooks. First, the FDA's at-home TMS approval fundamentally disrupts the traditional psychiatric revenue model. By moving neuromodulation out of the clinic and into the living room, we are witnessing the retail-ization of acute psychiatric care. This shifts the financial burden from high-margin clinical facilities to consumer electronics supply chains, rendering the traditional psychiatric hospital's capital expenditure on specialized TMS machines instantly obsolete and forcing a brutal consolidation of outpatient networks.
Second, the APA’s integration of digital phenotyping biomarkers into the DSM-5-TR marks a definitive pivot from subjective self-reporting to objective, continuous biometric surveillance. As Dr. John Torous, Director of the Digital Psychiatry Division at Beth Israel Deaconess Medical Center, recently stated, "Digital phenotyping transitions psychiatry from episodic guesswork to continuous, objective measurement." However, this creates a severe regulatory vacuum regarding data ownership, as smartphone keystroke dynamics and GPS mobility data are currently governed by consumer tech EULAs, not HIPAA, leaving patients exposed to unauthorized data brokering.
Third, the 40% premium hike by major US health insurers exposes the fatal flaw in the current psychopharmacology boom. The exponential rise in off-label GLP-1 use for binge eating and the integration of psychedelic-assisted therapies are collapsing the traditional actuarial models of employer-sponsored health plans. Insurers are no longer pricing for routine maintenance; they are pricing for high-cost, curative, and off-label neurological interventions, effectively pushing mid-market employers out of the comprehensive mental health coverage market and accelerating the shift toward direct-to-consumer cash-pay psychiatric services.
The Protectionist Mirage of Clinical Gatekeeping
Purists argue that the FDA’s approval of at-home, AI-driven TMS devices represents a dangerous deregulation of acute psychiatric care, stripping away the vital clinical oversight required to manage suicide risk and adverse neurological events. While clinically resonant, this argument ignores the stark mathematical reality of the provider shortage. With the national waitlist for a psychiatric evaluation exceeding six months in most metropolitan areas, the "safety" of the clinical gatekeeping model is merely a theoretical construct that results in actual patient harm through delayed intervention. The at-home TMS paradigm is not a compromise of clinical standards; it is a necessary triage mechanism to prevent systemic collapse in an era of unprecedented demand.
Echoes of the 1980s Prozac Paradigm
To contextualize the APA’s integration of digital phenotyping, observers must examine the introduction of the SSRI class, specifically Prozac, in the late 1980s. That historical pivot was predicated on the belief that shifting mental health treatment from psychoanalysis to targeted biological mechanisms would destigmatize care and democratize access. The modern iteration carries a critical distinction: the 1980s shift relied on patient self-reporting and subjective clinical interviews, whereas the 2026 shift relies on passive, algorithmic biometric surveillance. The enduring lesson from the SSRI era is that biological interventions often outpace our understanding of long-term neurological adaptation. We are now deploying algorithmic diagnostics without a robust framework for the psychological impact of being continuously monitored by one's own device.
The Efficacy Reality Check: Data Privacy vs. Algorithmic Determinism
Furthermore, the intense backlash against the use of smartphone keystroke dynamics for diagnostic purposes ignores the economic reality of digital health infrastructure. Privacy advocates argue that integrating consumer tech data into the DSM-5-TR creates an Orwellian surveillance state, commodifying mental health vulnerabilities for tech monopolies. This perspective fundamentally misunderstands the architecture of modern digital therapeutics. The integration of these biomarkers does not require the surrender of raw data to tech companies; rather, it utilizes localized, on-device edge computing to generate anonymized clinical alerts. The privacy imperative is not solved by banning the technology, but by mandating decentralized, zero-knowledge proof architectures that separate the diagnostic signal from the user's identity.
The High-Performance Premium: Sports and Showbiz Neuro-Insurance
Meanwhile, the launch of the $500M Neuro-Protection Trust by elite sports leagues and Hollywood studios represents the financialization of cognitive recovery. High-performance talent is no longer just protecting their physical assets; they are insuring their neurological baseline against the compounding effects of neuro-inflammation, concussive trauma, and algorithmic burnout. This trust effectively creates a parallel, private-tier psychiatric infrastructure for the elite, bypassing the public healthcare system entirely and establishing a new standard of care that relies on continuous, wearable neuro-telemetry rather than reactive clinical intervention.
Strategic Imperatives for Regional Health Systems
Local health systems, regional clinics, and citizens must immediately adapt to this bifurcated reality. For regional hospital networks, the strategic imperative is to pivot away from capital-intensive neuromodulation clinics and instead invest heavily in remote patient monitoring (RPM) infrastructure and biometric data interpretation. For citizens, the immediate action item is to audit the digital phenotyping permissions on their personal devices and actively opt into clinical-grade, HIPAA-compliant digital health registries rather than relying on consumer wellness apps. Diversifying personal health data ownership is no longer an optional privacy measure; it is a fundamental mechanism to ensure equitable access to next-generation psychiatric care.
The Six-Month Horizon: The Great Neurological Unbundling
Over the next six months, the mental health landscape will witness aggressive, highly publicized post-approval commercialization and regulatory scrambling. Expect the manufacturers of the newly approved at-home TMS devices to announce exclusive, value-based contracting agreements with major pharmacy benefit managers, effectively locking out independent clinics. Simultaneously, the Department of Health and Human Services (HHS) will be forced to issue emergency guidance on the classification of digital phenotyping data, likely creating a novel "biometric-privacy" pathway that will delay commercial digital-therapeutic deployments by 12 to 18 months. Most critically, the WHO’s report on adolescent dopamine downregulation will trigger a shadow regulatory war, with nations quietly drafting legislation to classify infinite-scroll algorithms as controlled neuro-hazards, fundamentally altering the valuation models of major social media conglomerates. The era of the generalized, episodic psychiatric monopoly is definitively over; the era of the hyper-fragmented, algorithmically monitored, and decentralized neuro-fortress has officially begun.
References:WHO Report on Algorithmic Impact on Adolescent NeurologyBeth Israel Deaconess Medical Center - Digital Psychiatry DivisionAmerican Psychiatric Association - DSM-5-TR Updates
Related Articles
The Great Psychiatric Recalibration: How Biometric Mandates, Psychedelic REMS, and AI Triage Are Rewiring the Mental Health Economy
Oct 31, 2026
The Neuro-Economic Inflection Point: How Regulatory Mandates and Algorithmic Surveillance Are Restructuring Behavioral Health
Oct 30, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account