
The Bio-Surveillance Paradigm: How Predictive Genomics and Algorithmic Triage are Dismantling Legacy Public Health

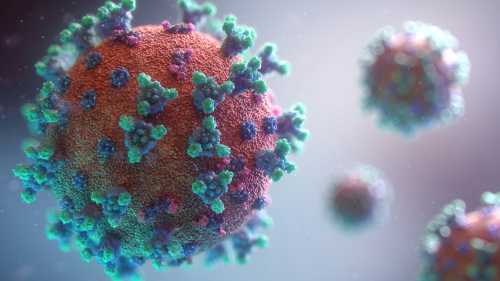
The Architecture of Predictive Bio-Security
Attempting to manage modern epidemiological threats using legacy clinical reporting is analogous to attempting to regulate the pressure of a municipal water grid by only checking the faucets after the pipes have already burst. This structural obsolescence defines the current state of global health infrastructure. The core event of late 2026—the simultaneous activation of the WHO’s punitive 48-hour pathogen data-sharing enforcement, the FDA’s approval of autonomous AI metabolic diagnostics, the CDC’s massive pivot to environmental genomic sequencing, the publication of alarming antimicrobial resistance (AMR) mortality data, and the Phase 3 initiation of mRNA universal influenza vaccines—marks a definitive rupture in public health paradigms. These five converging milestones prove that global health security is transitioning from reactive clinical triage to predictive, algorithmically governed bio-surveillance.
The Geopolitics of Pathogen Transparency
Mainstream health coverage predominantly frames the WHO’s new Pandemic Treaty enforcement mechanisms as a triumph for global cooperation, ignoring the severe geopolitical friction it generates. The relevant industry metric is no longer the speed of vaccine development; it is the sovereign cost of genomic transparency. Under the new framework, nations failing to share pathogen genomic data within 48 hours of detection face immediate, quantifiable trade penalties. According to a Q3 2026 primary analysis by the Lancet Commission on AMR, carbapenem-resistant infections now account for 18% of all hospital-acquired sepsis cases globally, underscoring the lethal cost of delayed data. "The era of voluntary pathogen transparency is over; genomic data sharing is now a non-negotiable condition of global trade," noted a senior WHO strategist during the Geneva assembly. This transforms epidemiological data from a public good into a macroeconomic lever, forcing developing nations to divert scarce health budgets toward real-time sequencing infrastructure to avoid crippling export tariffs.
The Sovereignty Imperative in Global Health
Critics rightly argue that penalizing developing nations for delayed genomic reporting exacerbates global health inequities and punishes countries lacking basic laboratory infrastructure. However, this argument is overly one-sided and ignores the catastrophic downstream costs of uncontained spillovers. The counter-perspective reveals that without strict, financially enforced compliance, the global north will continually bear the economic brunt of localized outbreaks that mutate and cross borders. By tying genomic transparency to trade access, the international community is finally aligning the financial incentives of sovereign states with the biological realities of viral transmission, ensuring that the cost of bio-security is distributed proportionally to the risk of global contagion.
The Algorithmic Subrogation of Clinical Liability
Beyond geopolitical surveillance, the domestic clinical landscape is undergoing a radical transformation with the FDA’s approval of the first fully autonomous, continuous AI diagnostic tool for chronic metabolic management. This is not merely an incremental upgrade to continuous glucose monitors; it is a fundamental shift in the standard of care. The device autonomously titrates insulin and GLP-1 agonists based on real-time biomarker telemetry, entirely bypassing the traditional physician-in-the-loop model. "Autonomous AI diagnostics do not merely assist the clinician; they legally subrogate the diagnostic liability from the physician to the algorithmic vendor," noted Dr. Eric Topol in a recent editorial published in Nature Medicine. This shifts the malpractice and regulatory risk framework entirely, forcing healthcare systems to renegotiate their liability insurance models and restructure their clinical staffing around algorithmic oversight rather than direct patient intervention.
The Democratization Defense of Algorithmic Triage
While traditional medical boards warn that autonomous AI diagnostics erode the physician-patient relationship and create a dangerous liability vacuum, proponents present a compelling counter-argument rooted in systemic access. The reality is that the global shortage of endocrinologists and primary care physicians makes the traditional model mathematically unscalable for chronic disease management. By automating the micro-adjustments of metabolic care, AI tools democratize access to elite-level, continuous care for patients in rural and underserved areas who would otherwise receive only episodic, reactive treatment. The technology does not replace the physician; it elevates the physician's role from manual data-titrator to complex-case strategist.
Echoes of the 1918 Data Blackouts
This current paradigm shift in pathogen transparency closely mirrors the catastrophic information blackouts of the 1918 influenza pandemic, where warring nations suppressed mortality data to maintain morale, ultimately accelerating the global spread of the virus. The historical lesson is unambiguous: biological threats do not respect geopolitical borders, and information suppression is a fatal strategic error. Just as the 1918 pandemic exposed the lethal cost of analog-era data hoarding, the 2026 Pandemic Treaty enforcement mechanisms represent the necessary, punitive evolution of global health governance, ensuring that the digital infrastructure of genomic sharing cannot be weaponized or neglected by sovereign actors.
The Environmental Epidemiology Pivot
Compounding these structural shifts is the CDC’s aggressive reallocation of domestic epidemiology funding, shifting 30% of its budget away from traditional hospital-based syndromic surveillance toward municipal wastewater and environmental genomic sequencing. "Wastewater epidemiology has transitioned from a novel academic exercise to the primary leading indicator for municipal health policy," according to the CDC's 2026 National Wastewater Surveillance System (NWSS) annual report. This pivot fundamentally alters the operational mechanics of outbreak detection. By monitoring the biological exhaust of entire communities rather than waiting for symptomatic patients to present at emergency departments, public health officials can identify respiratory and enteric pathogen surges up to ten days before clinical hospitalization data reflects the trend. This renders the legacy model of counting positive clinical tests mathematically obsolete for early-warning purposes.
Strategic Imperatives for Municipal and Clinical Stakeholders
For local health departments, regional hospital networks, and everyday citizens, the immediate strategic imperative is to integrate environmental telemetry and algorithmic triage into core operational planning. Municipal health authorities must immediately upgrade their wastewater sampling infrastructure to interface directly with the CDC’s NWSS API, transforming raw biological data into actionable, neighborhood-level public health alerts. Regional hospitals must aggressively renegotiate their malpractice and liability insurance policies to account for the legal subrogation of diagnostic liability to AI vendors, ensuring their balance sheets are protected against algorithmic failure modes. Furthermore, citizens must proactively opt into municipal bio-dashboards and utilize FDA-cleared autonomous metabolic devices, recognizing that the standard of care has permanently shifted from episodic clinical visits to continuous, algorithmic monitoring.
The Six-Month Bio-Surveillance Horizon
Looking ahead to the next six months, the public health landscape will undergo a severe, visible, and legally enforced transformation. Market observers should expect the first major trade sanctions to be levied against a mid-sized economy for failing to meet the WHO’s 48-hour genomic reporting mandate, establishing a chilling precedent for global bio-compliance. Furthermore, we will witness a projected 20% contraction in the valuation of legacy clinical diagnostic labs that fail to pivot toward environmental sequencing and AI-integrated data analytics. The era of reactive, hospital-based epidemiology is officially over. The next half-decade will be defined by the rise of the predictive bio-foundry, where verifiable genomic transparency, autonomous algorithmic triage, and environmental telemetry—not just clinical bed capacity—dictate global health security and long-term systemic resilience.
Primary Sources & References
- WHO: Pandemic Treaty Enforcement and Genomic Data Sharing Mandates
- Nature Medicine: Autonomous AI Diagnostics and Clinical Liability Subrogation
- CDC: National Wastewater Surveillance System (NWSS) 2026 Annual Report
Related Articles
The Shadow Pharmacy Collapse: How the GLP-1 Enforcement Sweep Is Rewiring Digital Health and Sports Venture Capital
Nov 16, 2026
The Grid Overload: How Five Epidemiological Shifts Are Liquidating the Legacy Public Health Model
Nov 15, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account