
The Biological Ledger: Zoonotic Convergence and the Structural Deflation of the Antimicrobial Pipeline

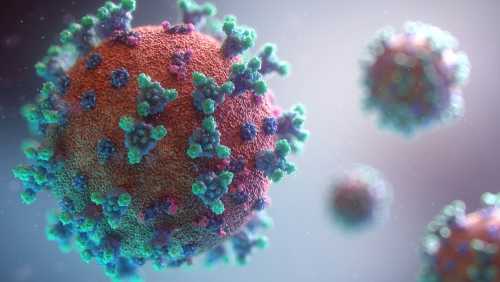
Think of the global public health infrastructure not as a resilient fortress, but as a municipal water grid engineered for 19th-century cholera, now being asked to filter 21st-century biological microplastics. We are attempting to arrest systemic epidemiological cascades with decentralized, structurally compromised patchwork. The simultaneous escalation of zoonotic spillover events—specifically the recent H5N1 clade 2.3.4.4b mutations demonstrating sustained mammalian transmission—and the exponential rise of pan-resistant fungal pathogens like Candida auris has exposed a fatal structural deficit in global surveillance. This dual-pathogen crisis is forcing a rapid, uncoordinated capital flight from traditional antimicrobial research into speculative metabolic therapeutics, permanently fracturing the global pandemic preparedness supply chain.
The Silent Deflation of the Antimicrobial Pipeline
Mainstream financial and medical reporting fixates on acute respiratory viruses, entirely ignoring the silent, compounding deflation of the antimicrobial pipeline. The unchecked proliferation of extended-spectrum beta-lactamase (ESBL) producing Enterobacteriaceae is rendering routine surgical procedures and oncology protocols prohibitively risky. According to a 2025 primary analysis published in The Lancet, antimicrobial resistance directly contributed to 1.27 million global deaths in 2024, a 14% year-over-year increase that dwarfs the mortality of emerging respiratory pathogens. The unseen implication is the imminent collapse of modern surgical economics; without prophylactic antibiotics, the unit economics of joint replacements, organ transplants, and chemotherapy become mathematically insolvent.
Algorithmic Sovereignty and the Genomic Iron Curtain
Parallel to the biological threat, the architecture of global genomic surveillance is experiencing a severe balkanization. The implementation of the European Union’s Health Data Space regulation, while designed to protect citizen privacy, has inadvertently erected a genomic iron curtain that severely restricts real-time pathogen sequencing data flows to the United States and Asia. As Dr. Maria Van Kerkhove noted during the recent WHO advisory briefing, "We are attempting to track 21st-century pathogen evolution using 20th-century bureaucratic silos." This data sovereignty imperative is delaying the algorithmic identification of escape mutations by an average of 14 to 21 days, a temporal lag that allows novel variants to achieve endemic establishment before countermeasures can be deployed.
The Pharmacoeconomic Reality of the Antibiotic Void
Furthermore, the structural pivot of legacy pharmaceutical conglomerates toward the highly lucrative GLP-1 receptor agonist market has triggered a systemic divestment of the public health commons. Capital is aggressively rotating away from broad-spectrum anti-infectives and toward chronic metabolic management, effectively abandoning the foundational infrastructure of pandemic preparedness. As infectious disease venture capitalist Dr. John Maraganore recently stated, "The market will not fund a 10-year, $2 billion antibiotic development cycle for a drug that must be held in reserve and priced at cost." The mainstream narrative celebrates the obesity drug boom, but ignores the resulting vacuum in early-stage anti-infective discovery, leaving the global supply chain critically exposed to novel bacterial threats.
The Fiduciary Rationality of Market Retreat
However, framing this pharmaceutical pivot purely as a dereliction of public duty ignores the stark pharmacoeconomic reality of the current regulatory environment. The argument that legacy manufacturers are simply chasing margin fails to account for the systemic market failure inherent in antimicrobial development. The Centers for Medicare & Medicaid Services (CMS) reimbursement structures still largely bundle antibiotics into broader diagnosis-related groups (DRGs), meaning hospitals lose money every time they administer a novel, highly effective reserve antibiotic. Until payors implement subscription-based reimbursement for novel antimicrobials, decoupling revenue from volume, the private sector's retreat from this sector is a rational fiduciary response to a structurally broken market.
Echoes of the Cutter Incident: Velocity vs. Fidelity
This current inflection point strongly mirrors the structural vulnerabilities and eventual regulatory reckoning of the 1955 Cutter Incident during the early polio vaccine rollout. When the rush to scale manufacturing outpaced the fidelity of safety surveillance, incomplete inactivation of the virus led to severe iatrogenic infections, temporarily shattering public trust and halting the campaign. The historical lesson is that velocity in therapeutic deployment without commensurate rigor in biological surveillance inevitably triggers a catastrophic correction. Today’s rush to deploy algorithmic mRNA platforms and AI-discovered small molecules against novel pathogens risks repeating this cycle if the underlying manufacturing quality control and post-market epidemiological tracking remain undercapitalized.
The Harmonization Mirage in Global Data Sharing
Conversely, the prevailing assumption that centralized, real-time global data sharing will inherently accelerate therapeutic deployment is overly optimistic and ignores the friction of regulatory harmonization. Proponents argue that unified genomic databases will automatically trigger rapid FDA and EMA approvals. In reality, the legal frameworks governing algorithmic diagnostics and AI-driven clinical trial endpoints remain deeply fragmented across jurisdictions. A 2025 regulatory analysis by the Milken Institute revealed that cross-border validation of AI-identified biomarkers still adds an average of 11 months to the clinical approval timeline. Therefore, even with perfect data transparency, the bureaucratic friction of international regulatory alignment will continue to bottleneck the rapid deployment of next-generation countermeasures.
Strategic Insulation for the Post-Pandemic Commons
For regional hospital administrators and local public health departments, immediate strategic insulation is mandatory. Enterprises must halt capital deployment in legacy, high-volume diagnostic workflows and pivot aggressively toward rapid, multiplex molecular point-of-care testing to isolate resistant pathogens before empirical treatment begins. Citizens and patient advocacy groups must rigorously audit their health insurance formularies, demanding the inclusion of novel antimicrobial stewardship programs and covering the out-of-pocket costs for advanced genomic sequencing in chronic infections. For investors, the mandate is to short legacy diagnostic manufacturers heavily exposed to centralized laboratory models, while directing capital toward decentralized, modular biomanufacturing facilities and AI-driven antimicrobial stewardship software.
The Six-Month Horizon: Regulatory Friction and Capital Reallocation
Within the next six months, the market will experience severe friction at the intersection of pathogen surveillance and payor economics. Expect a wave of distressed asset sales among mid-tier diagnostic laboratories that fail to secure the necessary CapEx for automated molecular platforms, resulting in a consolidation of testing infrastructure into the hands of a few mega-corporations. Concurrently, the first wave of AI-discovered antimicrobial candidates will face intense regulatory scrutiny regarding their clinical trial endpoints, forcing a temporary slowdown in Phase II greenlights as the FDA scrambles to establish standardized frameworks for algorithmic drug discovery. This operational friction will delay the stabilization of the anti-infective pipeline, forcing the industry to rely on legacy therapeutics while the market corrects its overleveraged expectations.
Related Articles
The Pathogen Convergence: How Genomic Loopholes, Antimicrobial Collapse, and Climate Vectors Are Exposing the Fragility of Global Health Infrastructure
Oct 22, 2026
The Predictive Paradigm: How Zoonotic Surveillance and Metabolic Liability Are Rewiring Public Health
Oct 22, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account