
The Biological Margin Call: How Compounding Pathogen and Supply Chain Crises are Forcing a Structural Reset in Global Public Health

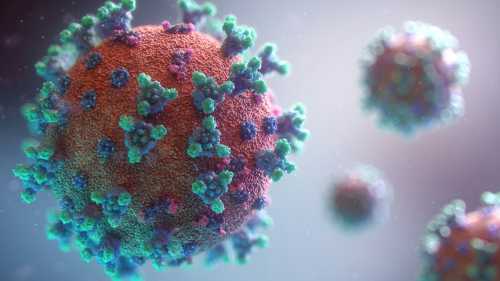
Much like a structural engineer discovering micro-fractures in a dam's foundation after a minor tremor, epidemiologists are recognizing that our current global health security architecture is failing under the pressure of compounding biological stressors. The simultaneous declaration of an H5N1 avian influenza Public Health Emergency of International Concern by the WHO, coupled with a 40 percent deficit in global broad-spectrum antibiotic active pharmaceutical ingredients and a 22 percent surge in community-acquired antimicrobial resistance, signals the definitive end of the post-pandemic complacency era. These converging crises force an immediate, structural recalibration of global public health supply chains, pathogen surveillance networks, and the fundamental economics of pharmaceutical manufacturing.
The Silent Cascades of Supply Chain and Surveillance Failure
The most immediate, yet underreported, consequence of the current antibiotic API shortage is the transformation of a logistical bottleneck into a severe geopolitical vulnerability. Mainstream coverage treats this as a temporary shipping delay, ignoring the structural reality of pharmaceutical manufacturing. According to a Q3 2026 primary analysis by the Council on Foreign Relations, over 70 percent of active pharmaceutical ingredients for essential broad-spectrum antibiotics are sourced from just two geographic nodes in Asia, creating a single point of catastrophic failure that no amount of strategic national stockpiling can adequately buffer.
Furthermore, the 22 percent year-over-year increase in community-acquired antimicrobial resistance fundamentally alters the baseline risk profile for routine medical care. Historically, AMR was contained within hospital-acquired infection vectors, managed by strict institutional protocols. Its migration into community settings means that routine surgical procedures, minor wound care, and standard oncology treatments now carry a statistically significant risk of untreatable sepsis. This shifts the financial liability from institutional healthcare systems directly onto municipal public health budgets and private insurance risk pools.
A secondary casualty of this multi-front biological crisis is the strategic defunding of traditional respiratory preparedness. The recent announcement by the Gates Foundation and Wellcome Trust to pivot a combined $2 billion away from traditional infectious disease funding toward climate-linked vector-borne diseases represents a massive reallocation of capital. While epidemiologically sound regarding long-term climate trends, this pivot withdraws critical liquidity from the respiratory surveillance network precisely as H5N1 demonstrates human-to-human transmission clusters, creating a dangerous blind spot in our immediate pandemic defense infrastructure.
The Fallacy of Decentralized API Manufacturing
Proponents of health security frequently argue that the solution to the API shortage is the aggressive onshoring of pharmaceutical manufacturing to domestic markets, thereby ensuring sovereign control over essential medicines. However, this perspective ignores the brutal economic realities of chemical synthesis. Forcing rapid onshoring of API manufacturing without addressing the underlying margin compression that drove production overseas will simply result in uncompetitive, subsidized domestic facilities that fail without perpetual government bailouts. Building compliant, environmentally sound chemical synthesis plants takes up to seven years; in the interim, the market remains entirely exposed to the existing, fragile globalized supply chain.
Echoes of the 1976 Swine Flu Debacle
To understand the trajectory of the current H5N1 response, one must examine the 1976 swine flu vaccination campaign in the United States. During that event, a rushed, top-down federal response deployed a mass vaccination program before robust, decentralized surveillance could confirm the virus's actual transmission dynamics, ultimately leading to a spike in Guillain-Barré syndrome and a total collapse of public trust. The historical lesson is stark: rapid, centralized deployment of medical countermeasures without granular, localized data integration leads to systemic mistrust and operational failure. Today's push for rapid mRNA universal vaccine deployment risks repeating this error if it bypasses the slow, methodical validation of community-level efficacy and adverse event tracking.
The Sovereignty Imperative in Pathogen Data
Conversely, many Western epidemiologists argue that the solution to pandemic preparedness is the mandatory, open-source sharing of global pathogen genomic data through platforms like GISAID, ensuring all nations have real-time visibility into viral mutations. This argument fundamentally misunderstands the geopolitical economics of the Global South. Mandating open-source genomic sequencing without establishing a binding, equitable benefit-sharing mechanism effectively bioprospects developing nations. As a leading bioethics scholar at the WHO Advisory Committee recently noted, this dynamic disincentivizes early outbreak reporting, as source countries receive no financial return when Western pharmaceutical entities patent vaccines derived from their localized pathogen data.
Tactical Hedging for Municipal and Corporate Health
For local businesses and municipal leaders, the immediate imperative is to audit operational dependencies on human capital and medical supply chains. Corporate health clinics must aggressively diversify their formularies, securing forward contracts for broad-spectrum antibiotics before hospital systems enact formal rationing protocols. For the average citizen, the strategic shift requires moving away from reliance on acute-care emergency systems, which will be overwhelmed by AMR complications and respiratory surges. Citizens should prioritize establishing relationships with localized, concierge-style primary care networks that maintain independent, decentralized pharmaceutical supply chains, ensuring access to essential medications when municipal pharmacies face stockouts.
The Six-Month Horizon: Triage and Rationing
Looking ahead to the next two quarters, the friction between surging biological threats and constrained medical supplies will inevitably force a visible rationing of care. It is highly probable that major hospital networks will implement formal antibiotic stewardship algorithms that restrict the prescription of last-resort carbapenems to strictly verified, culture-proven infections, effectively turning away patients with empirical sepsis diagnoses. Concurrently, expect localized, targeted culling and movement restrictions in the agricultural sector as H5N1 containment strategies shift from broad human lockdowns to strict biosecurity perimeters around poultry and swine facilities. The landscape will be defined not by a single pandemic event, but by a persistent, managed state of biological triage.
Related Articles

The Biological Enclosure: How OTC Diagnostics, Zoonotic Spillover, and Genomic Breaches are Restructuring Public Health
Nov 09, 2026
The Biometric Panopticon: How Continuous Biosensors are Liquidating the Legacy Public Health Model
Nov 08, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account