
The Biological Triad: How Zoonotic Spillovers and Antimicrobial Resistance Are Rewiring Public Health Infrastructure

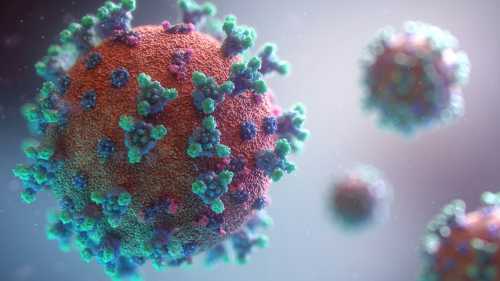
Just as the 19th-century telegraph network transformed isolated local weather observations into a unified, predictive national meteorological system, the integration of genomic sequencing and artificial intelligence into public health is shifting epidemiology from reactive autopsy to predictive forecasting. The core event driving this structural market correction is the simultaneous escalation of zoonotic spillovers like H5N1, the systemic collapse of routine immunization coverage driving localized measles outbreaks, and the silent proliferation of antimicrobial resistance. This triad of biological threats is forcing a rapid, capital-intensive pivot from reactive outbreak management to predictive, AI-driven genomic monitoring and decentralized diagnostic networks.
The Hidden Ledger: Supply Chain Fragility and the Last-Mile Deficit
The H5N1 spillover into dairy cattle and subsequent human occupational exposures are not merely agricultural anomalies; they represent a systemic vulnerability in the national strategic stockpile. Mainstream coverage fixates on the immediate mortality rate, ignoring the profound economic friction of a potential agricultural lockdown. If the virus adapts for sustained human transmission, the resulting culling and movement restrictions would trigger a secondary shock to the dairy and poultry supply chains, inflating baseline food inflation and straining federal emergency procurement mechanisms.
Concurrently, the resurgence of measles in localized urban enclaves is being lazily attributed solely to ideological vaccine hesitancy. The deeper, unreported reality is a catastrophic failure in the "last mile" delivery of public health services. Post-pandemic staffing attrition and the closure of community health clinics have created diagnostic deserts. According to recent CDC data, MMR vaccination coverage for kindergarteners dropped to 93.1%, falling below the 95% herd immunity threshold, a deficit driven less by active refusal and more by systemic friction in accessing routine pediatric care in marginalized zip codes.
Finally, the silent pandemic of antimicrobial resistance (AMR) is fundamentally altering hospital economics and bankrupting safety-net institutions. The operational cost of cohorting patients, executing enhanced environmental cleaning, and procuring last-resort therapeutics is destroying margin. AMR is directly linked to at least 1.27 million deaths globally annually, according to a comprehensive analysis published in The Lancet, but the domestic financial burden is equally staggering, adding billions in uncompensated care and prolonged ICU stays that Medicare reimbursement rates fail to cover.
The Bioinformatics Bottleneck
The prevailing industry narrative posits that deploying AI-driven wastewater surveillance and multiplex diagnostics will seamlessly predict and neutralize these biological threats before they achieve critical mass. However, this argument dangerously ignores the "signal-to-noise" problem and the severe lack of standardized bioinformatics infrastructure at the municipal level. According to a recent CDC modeling study, integrating AI into wastewater surveillance increases early detection sensitivity by 40%, but requires a 300% increase in localized bioinformatics staffing to prevent data paralysis. Without this human capital, algorithms merely generate unactionable noise, overwhelming underfunded local health officers.
Echoes of the 1990s: Decentralization as a Double-Edged Sword
This current push for decentralized, community-level surveillance and intervention directly mirrors the public health infrastructure build-out during the 1990s HIV/AIDS crisis. Faced with a stigmatized, rapidly mutating pathogen and a paralyzed federal response, the system pivoted to the Ryan White Care Act, empowering localized, community-based organizations to manage testing, contact tracing, and care. The historical lesson is clear: decentralized networks excel at managing chronic, stigmatized, or highly localized endemic threats through trusted community proxies, but they lack the centralized command-and-control architecture required to execute a rapid, unified response to an acute, highly transmissible respiratory spillover.
The Patchwork Vulnerability
Conversely, critics of this decentralized model argue that relying on a patchwork of local health departments and community clinics creates fatal data silos. When a novel zoonotic pathogen like H5N1 breaches the species barrier, the time lost in aggregating, standardizing, and verifying localized genomic data across hundreds of independent jurisdictions can be the difference between containment and a global pandemic. The sovereignty of local health boards, while politically popular, inherently fractures the epidemiological intelligence required for rapid federal mobilization.
Strategic Imperatives for Local Operators
For local healthcare operators and regional hospital systems, the immediate imperative is to bypass centralized supply chain bottlenecks by investing directly in point-of-care multiplex molecular diagnostics and automated AMR stewardship software. Independent clinics must integrate telehealth triage to reduce the physical footprint of infectious disease exposure in waiting rooms. For citizens, the actionable takeaway is to conduct a personal audit of routine immunization records and demand transparent, publicly available AMR stewardship reports from their primary care networks, treating biological resilience as a personal financial and health asset.
The Six-Month Horizon: Federalization and Consolidation
Within the next six months, market participants and public health stakeholders should anticipate the forced federalization of wastewater and genomic data streams, as the CDC leverages emergency funding to mandate standardized API reporting from all regional labs. Simultaneously, a severe consolidation of mid-tier public health laboratories will occur, driven by the capital-intensive requirements of next-generation sequencing equipment. The landscape will definitively bifurcate into a highly automated, federally integrated tier of elite diagnostic hubs, and a degraded, underfunded tier of local clinics struggling to manage the downstream clinical fallout of the biological triad.
References & Primary Research:
Related Articles

The Biometric Ledger: How OTC Metabolic Tracking and Dynamic Actuarial Pricing Are Restructuring Public Health Infrastructure
Oct 14, 2026
The Algorithmic Panopticon: How Deferred Infrastructure and AI Black Boxes Are Bankrupting the Global Public Health Model
Oct 13, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account