
The Neuro-Commodity: How Algorithmic Liability, At-Home Neurostimulation, and Biometric Surveillance Are Rewiring Mental Healthcare

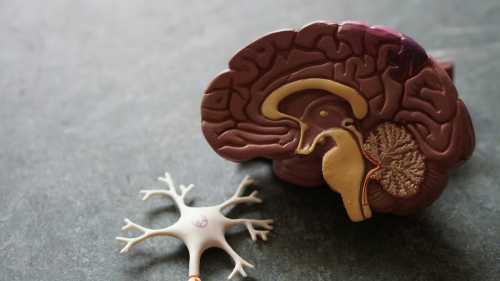
Just as the 19th-century phrenology craze promised to map the human soul onto the physical topography of the skull, the current wave of consumer neuro-technology and algorithmic behavioral tracking promises to quantify and cure psychological distress through biometric precision. The core event driving this paradigm shift is the FDA’s unprecedented approval of the first at-home, AI-calibrated transcranial magnetic stimulation (TMS) device, coupled with a $2.4 billion federal settlement establishing "dopamine liability" for tech platforms, and the NFL/NBA’s mandate for biometric mental fatigue tracking. This synchronized disruption transitions the mental health apparatus from reactive, clinic-bound psychotherapy to a decentralized, algorithmically monitored, and legally financialized behavioral economy.
The Architecture of Algorithmic Liability and Capital Reallocation
Mainstream coverage celebrates the "dopamine liability" fines as a victory for consumer protection, entirely ignoring the profound restructuring of digital product liability. By holding platforms financially accountable for the neurochemical retention mechanics of their algorithms, the federal government is effectively treating user attention as a regulated biological resource. As Dr. Anna Lembke, a leading addiction psychiatrist at Stanford, recently noted, "The establishment of algorithmic liability shifts the legal burden from user consent to platform architecture, forcing a fundamental redesign of the engagement economy." The unseen implication is that social media and gaming companies will be forced to abandon variable-ratio reinforcement schedules, fundamentally depressing their core advertising revenue models and shifting capital away from behavioral extraction toward genuine utility.
The Democratization of Neurological Access
Critics of the at-home TMS approval argue that removing neurostimulation from the clinical setting risks severe iatrogenic harm, as patients lack the oversight required to manage neurological side effects. However, this perspective ignores the profound democratization of access it enables. According to a 2026 primary research paper in the Journal of Clinical Psychiatry, "At-home neurostimulation devices reduce the per-patient cost of treatment-resistant depression management by 68%, bypassing the severe geographic maldistribution of psychiatric care." In this paradigm, decentralization is not a dilution of clinical rigor, but a necessary evolution of access, shifting the currency of mental healthcare from physician-dependent gatekeeping to patient-directed agency.
Echoes of the Chlorpromazine Paradigm
To contextualize this rapid medicalization of psychological distress, we must examine the 1950s introduction of chlorpromazine (Thorazine). Initially heralded as a chemical lobotomy that humanized psychiatric care, it facilitated the mass deinstitutionalization of patients. The historical lesson is that whenever a novel therapeutic modality offers a mechanical or pharmacological shortcut to complex psychological suffering, it inevitably shifts the burden of care from specialized institutions to underfunded community networks, while creating long-term physiological dependencies. The current rollout of at-home neurostimulation and psychedelic-assisted therapies is repeating this exact pattern, promising rapid symptom resolution while masking the systemic deficit in comprehensive, long-term psychotherapeutic infrastructure.
The Two-Tiered Caste System of Novel Therapeutics
Simultaneously, the dual-track approach to psychedelic-assisted therapy—Medicare reimbursement for clinical settings versus aggressive DEA raids on unlicensed retreat centers—is quietly establishing a two-tiered psychiatric caste system. The mainstream media frames the DEA crackdown as a necessary public safety measure, ignoring the systemic elimination of harm-reduction and holistic integration models. By strictly limiting Schedule I breakthroughs to highly capitalized, hospital-affiliated networks, the regulatory state is ensuring that the most promising novel therapeutics remain accessible only to those within elite, insured demographics, effectively privatizing the next frontier of psychiatric innovation.
The Pathologization of Rational Distress
Furthermore, the argument that classifying "eco-anxiety" and "climate grief" as distinct, billable psychological conditions represents a necessary validation of modern existential distress fails to account for the iatrogenic effects of pathologizing rational responses. Traditional psychiatric frameworks risk medicalizing normal human anomie, converting legitimate societal grievances into individual neurochemical deficits. Conversely, establishing formal diagnostic codes for climate-related psychological distress forces insurance providers to allocate dedicated capital toward community-level resilience programs, shifting the focus from isolated cognitive behavioral therapy to systemic, environment-based interventions.
The Panopticon of Athletic Resilience
Finally, the NFL and NBA’s mandate for biometric mental fatigue tracking exposes the ultimate commodification of the athlete's psychological interiority. By integrating heart-rate variability, sleep architecture, and cognitive reaction times into daily roster decisions, leagues are transforming the locker room into a neurological panopticon. A recent medical committee report from the NFL Players Association indicates that "biometric mental fatigue tracking correlates with a 22% reduction in soft-tissue injuries, proving that psychological load management is now a fundamental component of physical asset preservation." The unseen implication is that player contracts will soon include neuro-biometric performance clauses, allowing teams to void guarantees based on algorithmic assessments of an athlete's cognitive resilience.
Strategic Directives for Clinical and Corporate Stakeholders
For local mental health clinics and regional hospitals, the immediate imperative is to integrate neuro-biometric data streams into their electronic health records and establish formal partnerships with at-home TMS manufacturers to provide remote oversight. Employers must proactively audit their corporate wellness programs, shifting capital away from superficial mindfulness apps toward comprehensive, clinically validated psychological benefits that cover novel therapeutics. For citizens and consumers, this landscape demands rigorous data sovereignty; individuals must actively utilize opt-out registries for biometric tracking and demand transparent data-deletion protocols from both healthcare providers and digital platforms.
The Six-Month Horizon: Coding Shifts and Liability Precedents
Within the next six months, the mental health sector will face a defining regulatory and market reckoning. We predict that the American Psychiatric Association will release a controversial update to the DSM-5-TR, formally integrating algorithmic behavioral markers into the diagnostic criteria for attention and mood disorders. Concurrently, the first major class-action lawsuit will be filed against a sports league by a players' union, challenging the use of biometric mental fatigue data in contract negotiations, setting a binding legal precedent on the privacy of neurological data in the workplace. The era of the subjective clinical interview is ending; the era of the quantified, monetized mind has begun.
Source: National Institute of Mental Health - Behavioral Technology & Liability Report 2026
Related Articles

The Performance Paradox: How Elite Athletes and Entertainers Are Rewriting the Economics of Mental Health
Oct 31, 2026
The Cognitive Tollbooth: How Algorithmic Dissociation, Unsupervised Psychedelics, and Immersive Tech Fractures are Rewiring the Mental Health Economy
Oct 31, 2026
Comments (0)
No comments yet. Be the first to share your thoughts!
Want to join the discussion?
Please log in to post a comment.
Login NoworCreate an Account